
Pancreatic cancer treatment in Germany depends on the tumour stage, resectability, molecular characteristics, and the patient's overall health. Treatment may include surgery, chemotherapy, radiation therapy, precision medicine, and selected specialised approaches such as dendritic cell therapy, NanoKnife, TACE, and TACP. The article also covers prognosis, survival by disease extent, treatment costs, and practical considerations for international patients.
Complete Guide to Pancreatic Cancer Treatment in Germany
A pancreatic cancer diagnosis can raise difficult questions about what comes next and which treatment approach is most appropriate. Because every patient's situation is different, care is planned around the characteristics of the cancer, the patient's overall condition, and how the disease responds as treatment progresses.
Pancreatic Cancer Symptoms, Causes and Risk Factors

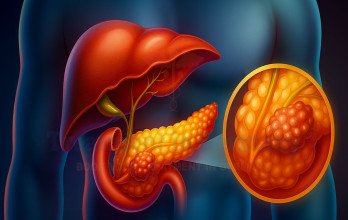
Pancreatic cancer is often quiet in its early stages, which is why pancreatic cancer symptoms and causes deserve attention when they persist. The pancreas sits deep in the abdomen, so a small tumour rarely causes obvious signs until it affects nearby structures such as the bile duct or because of the systemic effects of the disease. NCI similarly emphasizes that early disease often produces few or nonspecific symptoms
Common symptoms and warning signs tend to appear as the tumour grows:
- Painless yellowing of the skin or eyes (jaundice), often with dark urine and pale stools.
- Upper abdominal or mid-back pain that may worsen after eating or when lying down that may radiate to the back.
- Unintended weight loss and loss of appetite.
- New-onset diabetes, or diabetes that suddenly becomes hard to control, especially with weight loss.
Less common symptoms can still be meaningful, particularly in combination:
- Greasy, floating stools that are hard to flush (a sign of poor fat digestion).
- Nausea, bloating, or early fullness after small meals.
- Unexplained blood clots in a leg vein.
- Persistent itching, usually linked to blocked bile flow.
The causes are multifactorial. Most cases are pancreatic adenocarcinoma, which accounts for more than 90 percent of pancreatic cancers, and its risk rises with age and certain exposures. Smoking is the most consistent modifiable risk, while chronic pancreatitis, long-standing diabetes, and obesity also increase risk [1].
Family history and genetic factors matter for a meaningful minority of patients:
- Inherited changes in BRCA1 or BRCA2, PALB2, or Lynch syndrome genes raise risk and can influence treatment choices later
- A strong family history of pancreatic, breast, ovarian, or colorectal cancer is worth discussing with a specialist.
- Hereditary pancreatitis carries a notably higher lifetime risk.
Lifestyle and environmental risk factors are the ones patients can most often act on:
- Tobacco use, heavy alcohol intake, and excess body weight.
- Other possible environmental and dietary associations have been studied, but the evidence is less consistent than for established risk factors such as smoking, obesity, chronic pancreatitis, and certain inherited conditions.
Symptoms require medical evaluation when jaundice appears, when abdominal or back pain is persistent and unexplained, or when weight loss and new diabetes occur together. These symptoms can have causes other than cancer, but persistent or unexplained symptoms should be medically evaluated so that the cause can be identified and treated appropriately.
Types of Pancreatic Cancer

Pancreatic tumours are not a single disease. They differ in the cells they arise from, how they behave, and how they are treated, so identifying the type of pancreatic cancer is a first step that shapes everything after it. Exocrine pancreatic cancers arise from the cells that make digestive enzymes and make up the large majority of cases. Pancreatic adenocarcinoma (ductal adenocarcinoma) is the most common exocrine tumour, representing over 90 percent of pancreatic cancers, and it tends to grow and spread more aggressively than other subtypes [1].
Pancreatic neuroendocrine tumors (pNETs) are far less common, often grow more slowly, and can produce hormones. They follow different treatment pathways and generally carry a better outlook than adenocarcinoma, so pancreatic NET treatment in Germany may involve different approaches depending on tumour grade, hormone production, receptor status, and disease extent.These tumour types differ in how quickly they grow and spread, so their treatment plans can be different. The treatment approaches described below primarily apply to pancreatic ductal adenocarcinoma, the most common exocrine pancreatic cancer. Pancreatic neuroendocrine tumours have different treatment pathways and may require different surgery, systemic therapy, or hormone-directed treatment. For selected pancreatic NETs with appropriate receptor expression, Lutetium-177-DOTATATE may be considered as a peptide receptor radionuclide therapy. Confirming the type through pathology is therefore essential before any plan is finalised.
Pancreatic Cancer Diagnosis and Staging Tests

Diagnosis of pancreatic cancer may involve imaging, tissue sampling, and laboratory tests to determine whether cancer is present, identify its type, and assess how far it has spread. These findings help guide the treatment plan.
- Blood tests and tumor markers: can support the evaluation of pancreatic cancer, and CA 19-9 may be useful for monitoring treatment response when it is elevated. However, CA 19-9 is not specific enough to diagnose pancreatic cancer or to be used as a screening test on its own.
- Ultrasound: may help identify bile duct blockage or other abnormalities, particularly when jaundice is present. CT or MRI is generally used for more detailed assessment of a suspected pancreatic tumour.
- CT and MRI: a dedicated pancreatic-protocol CT, sometimes with MRI and MRCP, maps the tumour and its relationship to nearby blood vessels.
- Endoscopic ultrasound (EUS): brings the probe close to the pancreas and allows a guided needle biopsy in the same session.
- Biopsy and pathology: confirms the diagnosis and subtype; EUS-guided biopsy is a highly accurate way to obtain tissue, and modern core-needle sampling further improves diagnostic accuracy [2].
- Molecular and biomarker testing: checks the tumour and, where relevant, inherited genes to find changes that open the door to targeted therapy.
Together these tests establish treatment options by defining tumour type, stage, and biology. In one 2025 retrospective study, actionable alterations were identified in about one in five patients, and these findings influenced treatment selection in some patients [3].

How diagnosis moves from first tests to a defined treatment plan.
Pancreatic Cancer Stages and Surgical Resectability
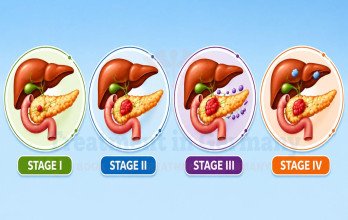
Staging describes how far the cancer has spread, from a tumour confined to the pancreas through to disease that has reached distant organs. Alongside the numbered stage, surgeons use a second, practical grouping that decides whether an operation is possible now.
- Stage I: disease is confined to the pancreas and may be removable with surgery, depending on tumour location and its relationship to nearby blood vessels.
- Stage II: disease may involve a larger tumour or nearby lymph nodes and can still be resectable in some patients, depending on tumour location and involvement of nearby blood vessels.
- Stage III: pancreatic cancer may involve major nearby blood vessels or four or more regional lymph nodes. When the tumour is locally advanced and cannot be completely removed, selected patients may be reassessed for surgery after systemic treatment.
- Stage IV: cancer has spread to distant sites such as the liver, lungs, or the abdominal lining.
The pancreatic cancer staging and resectability assessment is where treatment planning becomes concrete. Tumours are classified as resectable, borderline resectable, or unresectable based on their relationship with nearby major blood vessels, surrounding structures, and whether complete tumour removal is technically feasible. This classification helps determine whether the initial approach involves surgery, systemic treatment, or a combination.

Reported proportions at diagnosis include 10–20% resectable disease, 5–10% borderline-resectable disease, 30–40% locally advanced or unresectable disease, and 50–60% metastatic disease. These figures come from different reported ranges and should not be added together [6].
Pancreatic Cancer Treatment Approaches in Germany

Most patients receive more than one type of treatment, sequenced by a specialist team. Treatment is selected and sequenced according to the cancer's stage, resectability, tumour biology, and the patient's overall health.
Pancreatic Cancer Surgery: Curative and Palliative
Surgery for pancreatic cancer offers the best chance of long-term control when the tumour can be fully removed, so careful selection is central. The operation depends on where the tumour sits in the pancreas.
- Whipple procedure (pancreaticoduodenectomy): for tumours in the head of the pancreas; removes the head, part of the duodenum, and nearby structures.
- Distal pancreatectomy: for tumours in the body or tail, often with removal of the spleen.
- Total pancreatectomy: removes the whole pancreas in selected cases, with lifelong pancreatic enzyme replacement and insulin treatment afterwards. Other surgical approaches may include minimally invasive surgery or vascular reconstruction in carefully selected patients, depending on tumour location, blood-vessel involvement, and whether complete tumour removal is technically possible.
- Bypass or stent procedures relieve a blocked bile duct or stomach outlet when the tumour cannot be removed.
Surgery has a role beyond clearly operable disease. Borderline-resectable or locally advanced tumours may become candidates for surgery after systemic treatment in selected patients. Reassessment at an experienced pancreatic centre can help determine whether complete removal is feasible. When cure is not the goal, focused procedures still ease symptoms and protect quality of life.
Chemotherapy and Systemic Therapies for Pancreatic Cancer
Chemotherapy for pancreatic cancer is the backbone of pancreatic cancer treatment and is used at almost every stage. Its timing is what changes.
- Neoadjuvant chemotherapy is given before surgery to treat possible microscopic disease early, assess how the cancer responds, and improve the chance of successful complete removal in appropriate patients.
- Adjuvant chemotherapy follows surgery to lower the risk of the cancer returning.
- For locally advanced disease, systemic chemotherapy is a major part of treatment and may make surgery possible in selected patients whose tumours respond sufficiently.
- For metastatic disease, combination chemotherapy is commonly used in patients who are fit enough to tolerate it, while less intensive treatment or symptom-focused care may be appropriate for patients with poorer overall health.
Common regimens include FOLFIRINOX and gemcitabine with nab-paclitaxel, chosen according to fitness and goals. In one study of patients with borderline-resectable pancreatic cancer, neoadjuvant FOLFIRINOX was associated with longer median overall survival than upfront surgery, 19.8 versus 10.6 months. Because the study involved a selected patient group, these results should not be interpreted as an expected survival time for every patient. Selected patients also receive targeted or systemic drugs matched to their tumour, discussed further below [4].
Radiation Therapy, Chemoradiation and SBRT Options
Radiation therapy for pancreatic cancer is used selectively rather than routinely, and it is chosen for specific clinical situations. It can improve local tumour control in selected situations or relieve symptoms when a tumour affects nearby structures.
- Radiation may be considered for locally advanced tumours that remain unresectable after chemotherapy.
- It also has a role in selected resectable or borderline resectable disease as part of a combined plan.
- Chemoradiation pairs radiation with chemotherapy to improve local effect.
- Stereotactic body radiation therapy (SBRT) delivers precise, high-dose radiation over a few sessions, sparing surrounding tissue.
- Radiation can ease pain and control bleeding when symptom relief is the priority.
Pancreatic Cancer Targeted Therapies and Precision Medicine
Precision medicine matches treatment to specific changes found in a tumour and is an important part of treatment planning for many patients with advanced disease. Testing looks for changes that can be targeted with a specific drug or that predict a strong response to particular chemotherapy.
- Biomarker-driven treatment begins with molecular and, where relevant, inherited genetic testing, which can help identify patients who may benefit from targeted therapy for pancreatic cancer.
- Relevant findings may include BRCA1/2 or PALB2 alterations, mismatch-repair deficiency or microsatellite instability, NTRK or other actionable gene fusions, and other tumour-specific alterations that may have a matched treatment option.
- Matched targeted therapy may include maintenance olaparib for selected patients with metastatic pancreatic cancer who have germline BRCA1/2 variants and whose disease has not progressed after first-line platinum-based chemotherapy.
- Immunotherapy for pancreatic cancer may be an option for the small subset of patients whose tumours are microsatellite instability-high (MSI-H) or mismatch-repair deficient (dMMR).
- Genetic and tumour testing can help identify patients who may benefit from matched treatment options and help guide treatment selection.
Molecular profiling can identify a treatment-relevant alteration in a subset of patients. In a 2025 retrospective study, actionable alterations were identified in 20% of patients, and those who received molecularly matched treatment had a median overall survival of 32.9 months from metastatic diagnosis. Because these results came from a selected observational cohort, they show an association rather than a guaranteed benefit for every patient [3].
Specialized and Interventional Pancreatic Cancer Therapies in Germany

Eligible patients in Germany may be considered for several specialized and interventional pancreatic cancer therapies:
- Dendritic cell therapy for pancreatic cancer is a personalised immune-based approach that may be considered for selected patients as part of an individual treatment plan.
- NanoKnife treatment for pancreatic cancer is a non-thermal local ablation technique that may be considered for selected patients with locally advanced pancreatic cancer, including tumours near major blood vessels. Treatment suitability depends on tumour location, disease extent, previous treatment, and overall health [5].
- TACE for pancreatic cancer and TACP for pancreatic cancer are specialised catheter-based locoregional approaches that may be considered for selected patients at experienced centres, depending on tumour location, previous treatment, overall health, and the treatment plan.
- Other locoregional techniques may also be used for local control or symptom relief in selected patients.
Which patients may be evaluated depends on tumour location, response to earlier chemotherapy, overall fitness, and the absence of widespread disease. Because these therapies are specialized, suitability is decided case by case at experienced centres.
Metastatic and Recurrent Pancreatic Cancer Treatment

When pancreatic cancer has spread, treatment focuses on controlling the disease, extending life, and maintaining comfort. Roughly half of patients already have metastatic disease at diagnosis, most often involving the liver [6].
- Stage 4 pancreatic cancer treatment is led by systemic therapy, since the disease is no longer confined to one area.
- Pancreatic cancer with Liver metastases is managed mainly with chemotherapy, with local options in selected cases.
- Other sites, such as the lungs or the abdominal lining, are treated within the same systemic strategy.
- A small number of highly selected patients with limited metastatic disease may be evaluated for local or locoregional treatment alongside systemic therapy, usually within specialist treatment strategies.
Recurrent disease, meaning cancer that returns after earlier treatment, is assessed afresh. The team weighs where and when it came back, previous therapies, and current fitness before choosing between further chemotherapy, a matched targeted approach, or a locoregional technique.
Pancreatic Cancer Survival Rates, Life Expectancy, and Prognosis
Prognosis in pancreatic cancer depends heavily on stage at diagnosis and whether the tumour can be removed. Across all stages, the current five-year relative survival for pancreatic cancer is 13.7%. Survival also varies according to the extent of disease at diagnosis. Current SEER data report a five-year relative survival of 43.6% for localized pancreatic cancer, 17.0% for regional disease, and 3.4% for distant metastatic disease. These figures are population estimates and cannot predict an individual patient's outcome [7].
Survival is generally better when pancreatic cancer is found before it has spread, although individual outcomes also depend on tumour biology, resectability, overall health, treatment response, and the treatments available.

Reported median survival across selected scenarios and studies. Populations differ, so the bars are not a direct comparison [3] [4].
Factors affecting prognosis go beyond the stage number:
- Whether complete surgical removal is achieved, and the tumour margins afterwards.
- Response to treatment, assessed through imaging and, when CA 19-9 is elevated and clinically useful, changes in its level.
- Tumour biology, including targetable genetic changes.
- Overall health and ability to tolerate treatment.
Resectability and response to treatment are important factors that influence prognosis. Neoadjuvant chemotherapy before surgery has been associated with improved survival in selected patients with borderline-resectable disease. In a retrospective study, molecularly matched treatment was associated with longer median survival in a selected patient group. Recurrence remains common, so long-term follow-up is part of the plan. Individual prognosis varies because no two tumours, or two patients, are the same [3] [4].
Pancreatic Cancer Treatment Costs in Germany
Pancreatic cancer treatment cost depends on the plan rather than a single price, because pancreatic cancer care is highly individual. A patient who needs surgery followed by chemotherapy will have a different cost profile from one whose care centres on systemic therapy.
- The type and number of treatments (surgery, chemotherapy cycles, radiation, or specialized procedures) is the largest driver.
- Diagnostics and hospital stay, including imaging, biopsy, pathology, and any intensive-care time after major surgery.
- Supportive care, such as nutrition support and management of side effects.
- Follow-up imaging and laboratory monitoring over time.
For international patients, health insurance coverage varies by country and policy, and many arrange care on a self-funded or insurer-approved basis. Because the plan is built around the individual tumour and stage, a precise estimate is prepared only after the diagnostic review, when the recommended treatments are known.
Why Choose Germany for Pancreatic Cancer Treatment?
German pancreatic cancer centres may bring together surgeons, medical oncologists, radiation oncologists, radiologists, pathologists, gastroenterologists, and other specialists to develop an individual treatment plan.
- Specialist pancreatic cancer centres with experienced surgical teams and high procedure volumes, which may be associated with better outcomes for complex operations.
- Multidisciplinary teams where surgeons, oncologists, radiologists, and pathologists plan care together.
- Experienced pancreatic surgeons and oncology specialists focused on this disease.
- Advanced diagnostics, including high-resolution imaging, endoscopic ultrasound, and molecular profiling.
- Modern surgical and treatment technologies, from minimally invasive surgery to precise radiation and specialized ablation.
- Personalized treatment planning that reflects tumour biology and patient goals.
- Structured international patient support for language, logistics, and coordination.
Pancreatic Cancer Treatment Process in Germany
For international patients in Germany, the process commonly begins with a review of existing medical records before travel. Any additional diagnostic tests are then arranged in Germany, followed by treatment planning, treatment, and follow-up.
- Medical records and case review: reports, pathology, and imaging are assessed remotely, often producing an early opinion before travel.
- Diagnostic evaluation: any missing tests, such as updated imaging, biopsy, or molecular profiling, are completed on arrival.
- Multidisciplinary treatment planning: the tumour board agrees a personalised plan.
- Treatment: surgery, chemotherapy, radiation, or specialized therapy proceeds as scheduled.
- Monitoring and follow-up: response is tracked with imaging and CA 19-9, and the plan is adjusted as needed.
- Post-treatment care: recovery support, nutrition, and a follow-up schedule are arranged, including handover to the home physician.

The treatment journey for international patients, from first contact to follow-up.
Planning pancreatic cancer treatment in Germany starts with a clear understanding of your medical case. International patients can submit their medical reports and imaging for review, receive guidance on suitable treatment options, and get support with appointments, visa documentation, travel arrangements, and interpretation. Contact TIG GmbH (Treatment in Germany) to discuss your case and take the next step toward treatment in Germany.
References
Why Patients Worldwide Prefer Our Medical Services in Germany – Key Benefits Explained











.webp)
 (1).webp)

.webp)


.jpg)

 (1).webp)


.jpg)