
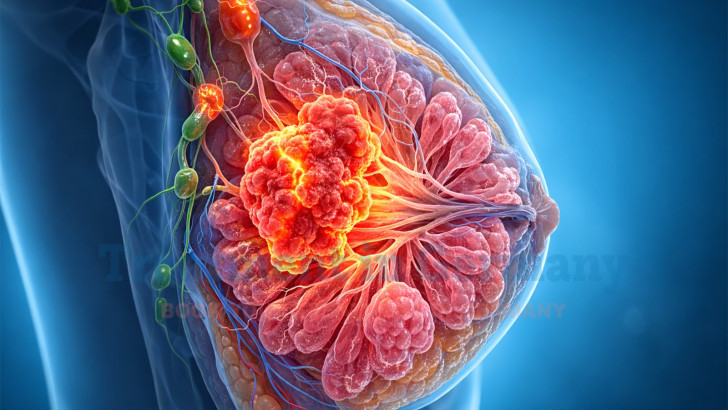
Metastatic breast cancer treatment in Germany is individualized according to tumor biology, biomarker results, disease characteristics, and previous treatment. This guide covers biomarker reassessment, systemic and targeted therapies, site-directed treatments, treatment monitoring, and supportive care as part of a coordinated approach to managing Stage 4 breast cancer.
Stage 4 Breast Cancer Treatment in Germany
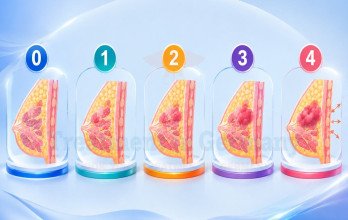
Metastatic, or Stage 4, breast cancer is generally not considered curable. Treatment therefore focuses on controlling the disease, managing symptoms, and maintaining quality of life for as long as possible [1]. In Germany, treatment is guided by national clinical guidelines and individualized according to the cancer's subtype, biomarkers, previous treatments, and the patient's overall clinical condition. For an overview of available treatment approaches, see our guide to breast cancer treatment in Germany.
Treatment options include hormone-based and HER2-targeted therapies, immunotherapy, antibody-drug conjugates, PARP inhibitors, and biomarker-directed targeted therapies. These treatments are selected according to tumor subtype, biomarkers, prior treatment, and clinical circumstances. Because these factors differ from person to person, there is no single treatment plan for everyone.
Personalized Treatment for Metastatic Breast Cancer
The treatment plan is reviewed and adjusted more often than in early-stage disease, guided by how the cancer responds and how well the patient tolerates therapy.
Disease that is metastatic from the outset (de novo) is generally assessed in full before a first treatment is chosen, while a recurrence after earlier treatment can draw on how the tumor previously responded to chemotherapy, endocrine therapy or HER2-directed treatment.
Several factors are weighed together when a treatment plan is built:
- Extent and location of disease: limited (oligometastatic) or widespread, and which organs are involved.
- Hormone receptor (ER, PR) and HER2 status, together with other clinically relevant biomarkers, which help determine which systemic therapies may be appropriate.
- Previous treatment and how the tumor responded.
- Symptoms and overall health, including organ function and treatment tolerance.
- The patient's own treatment goals and priorities.
Because of this, two patients with the same original diagnosis can receive different therapies, depending on breast cancer subtype, receptor status, other biomarkers, previous treatment, and the pattern of metastatic disease [1] [2].
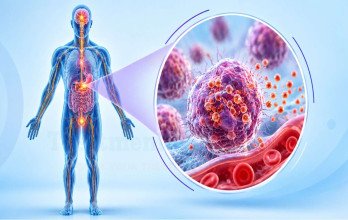
Systemic therapy is the main treatment for metastatic breast cancer because the disease may be present beyond the sites visible on imaging. Radiation and, in selected cases, surgery may also be used to treat specific areas causing symptoms or at risk of complications, alongside rather than instead of systemic treatment, though their role varies according to the clinical situation. Because metastatic breast cancer can eventually progress despite treatment, many patients receive different lines of therapy over time.
Reassessing Metastatic Breast Cancer for Treatment

A new metastasis or suspected recurrence should be evaluated in the context of the patient's clinical history and imaging findings before treatment is changed. Because tumor biology can change over time, guidelines recommend, where feasible, biopsying a metastatic site to confirm the diagnosis and re-evaluate receptor status. If a biopsy is not safe or possible, imaging and clinical assessment can support the diagnosis, and blood-based molecular testing may add information when actionable mutations are being considered, although a negative blood test does not exclude an alteration and tissue testing remains important [2].
Reassessment typically covers:
- ER, PR and HER2 testing repeated on the metastatic tissue
- Molecular or genomic testing used where a targeted therapy might depend on the result
- Imaging used to map disease extent
- Review of previous treatments, including how well the cancer responded to each
These findings can meaningfully change the treatment plan, which is why reassessment is not treated as a formality even when a patient’s original diagnosis seems well established.
Biomarker and Receptor Reassessment
ER, PR, and HER2 status can change between the original tumor and a later metastasis, a phenomenon known as receptor conversion. Current guidelines therefore recommend re-testing when possible rather than relying on results from years earlier [3].
For example, a tumor initially classified as HER2-negative may show HER2 IHC 1+ or IHC 2+/ISH-negative expression on a later specimen, which may have treatment implications. While this is not considered HER2-positive disease, it may affect eligibility for certain HER2-directed antibody-drug conjugates, depending on tumor subtype and previous treatment.
Further testing depends on the tumor subtype, treatment history, and therapies being considered. This may include BRCA1/2 testing and selected alterations such as PIK3CA, AKT1, PTEN, ESR1, or NTRK, as well as PD-L1 testing in appropriate cases of triple-negative breast cancer when immunotherapy is being considered. ESR1 mutations can emerge during endocrine therapy and are often detected through blood-based testing, potentially guiding the choice of subsequent endocrine treatment.
Imaging and Metastatic Disease Assessment
CT, bone scans, MRI and, in some cases, PET-CT are used based on the suspected sites of spread, since bone, liver, lung and brain metastases are not equally visible on every method. Before treatment begins, imaging establishes a baseline disease burden for comparison; during treatment, repeat imaging at intervals set by the oncologist shows whether the cancer is responding, stable or progressing, and additional imaging may be needed sooner if new symptoms develop [3].
Systemic Treatment Choices for Metastatic Breast Cancer

The choice and sequence of systemic treatment are guided mainly by the tumor’s biology, biomarkers, previous treatments, symptoms, and how quickly the cancer needs to be controlled.
- Hormone receptor-positive, HER2-negative disease: For patients with hormone receptor-positive, HER2-negative metastatic breast cancer who do not require an urgent tumor response, treatment typically centers on hormone and targeted therapy for breast cancer, with endocrine therapy generally preferred over chemotherapy. It is often combined with a CDK4/6 inhibitor such as palbociclib, ribociclib, or abemaciclib. The choice of endocrine partner depends on factors such as menopausal status and ovarian function, previous endocrine exposure and response, the timing of recurrence, other disease characteristics, and the overall treatment strategy [3].
- HER2-positive disease: Treatment is based on HER2-targeted therapy, with the regimen selected according to the clinical situation and previous treatment. Trastuzumab plus pertuzumab with a taxane remains an established first-line option. In September 2026, the European Commission also authorized trastuzumab deruxtecan plus pertuzumab for the first-line treatment of eligible adults with unresectable or metastatic HER2-positive breast cancer [10]. In the DESTINY-Breast09 trial, this combination significantly prolonged progression-free survival compared with the standard regimen [4]. Treatment selection depends on previous therapy, disease characteristics, tolerability, and applicable German recommendations. Later treatment depends on previous HER2 therapies, response, and whether the cancer has spread to the brain; tucatinib-based combinations may be particularly useful when brain metastases are present [2].
Triple-negative breast cancer (TNBC): Chemotherapy remains an important part of treatment. For eligible patients whose tumors are PD-L1 positive (CPS ≥10), first-line options include immunotherapy for breast cancer, such as pembrolizumab combined with chemotherapy. Following its European Commission authorization in August 2026, sacituzumab govitecan combined with pembrolizumab is also a first-line option for adults who have not received prior systemic therapy for metastatic disease [3] [5] [6] [8] [9].
- Chemotherapy: Chemotherapy can be used across breast cancer subtypes, especially when hormone-based or targeted treatments are no longer effective or when rapid disease control is needed, such as in visceral crisis (severe organ dysfunction caused by the cancer).
- Antibody-drug conjugates (ADCs): These drugs combine a targeted antibody with a cancer-killing payload. Examples include trastuzumab deruxtecan, sacituzumab govitecan, and datopotamab deruxtecan. Their use depends on factors such as HER2 expression, tumor subtype, biomarkers, and previous treatment.
- PARP inhibitors:Olaparib and talazoparib may be used in selected patients with HER2-negative metastatic breast cancer who have a confirmed germline BRCA1/2 mutation. Having a BRCA mutation alone does not automatically mean a PARP inhibitor is appropriate; eligibility also depends on the specific drug and previous treatments [3].
- Bone metastases: Bone-modifying treatment such as bisphosphonates or denosumab may be used to reduce bone complications (see the bone metastases section below).
Treatment is not one fixed sequence. What comes next depends on how the cancer responds, which treatments have already been used, side effects, new biomarker information, and the patient's overall condition. The final choice is made by the treating oncology team, and because regulatory status for newer indications can change, it should be confirmed before treatment decisions are made. Authorization in the EU does not by itself determine availability or reimbursement in an individual case.
Treatment by Breast Cancer Subtype
First-line systemic treatment for metastatic breast cancer depends on the tumor subtype, biomarker results, previous treatment, and the need for rapid disease control. Common approaches include endocrine therapy plus a CDK4/6 inhibitor for hormone receptor-positive, HER2-negative disease; HER2-directed treatment for HER2-positive disease; and immunotherapy-based regimens or selected antibody-drug conjugates for eligible patients with triple-negative breast cancer. Brain metastases, overall health, and treatment eligibility can also influence the choice.

The table above summarizes selected first-line systemic treatment options for each metastatic breast cancer subtype and the main factors guiding treatment selection.
Treatment for Breast Cancer Metastases by Site

Where breast cancer has spread also influences treatment, and site-directed treatment is added when a metastasis is causing symptoms, threatens a structure such as the spine, or could benefit from local control. In carefully selected patients with few metastatic sites (oligometastatic disease), local treatment directed at those sites alongside continued systemic therapy may be considered, decided individually [2].
Bone Metastases and Bone Complications
Bone is one of the most common metastatic sites. Alongside systemic treatment, bone-modifying drugs such as bisphosphonates or denosumab reduce the risk of skeletal-related events, including fractures, and the schedule is individualized according to disease status, previous treatment, side effects, and ongoing benefit [2]. Specific interventions may include radiation for painful lesions or those at risk of fracture, surgery for selected structural complications, and ongoing pain management adjusted as the disease evolves.
Before and during bone-modifying treatment, the care team may assess dental health, calcium levels and kidney function, as appropriate to the selected medicine, to reduce the risk of treatment-related complications .
Spinal cord compression is an oncologic emergency. In people with known or suspected cancer, new limb weakness, difficulty walking, sensory changes, or bladder or bowel dysfunction require immediate medical assessment. New, severe or worsening back pain also needs urgent clinical evaluation, particularly when accompanied by neurological symptoms, because spinal metastases may threaten spinal stability or lead to cord compression [7].
Brain Metastases and Neurological Disease
Brain metastases require individualized planning involving medical oncology, radiation oncology, neurosurgery, and neuroradiology as appropriate. Local treatment is selected according to the number, size, location, symptoms, and overall disease status: stereotactic radiosurgery is commonly used for a limited number of small, suitable brain metastases, while whole-brain radiotherapy or surgery may be appropriate in selected situations, such as widespread involvement or a single large, symptomatic or diagnostically uncertain lesion.
In HER2-positive disease, systemic treatments with intracranial activity, including trastuzumab deruxtecan and tucatinib-based combinations, may also be appropriate, depending on previous therapy and treatment eligibility. Deferring local treatment may be considered only in selected situations following specialist multidisciplinary assessment [2] [3]. New headache, seizures, weakness, or changes in vision or cognition should be reported promptly.
Liver and Lung Metastases
Systemic therapy is the primary treatment for liver and lung metastases in most patients. In carefully selected cases, a locoregional, liver-directed approach may be added to systemic treatment rather than replacing it.
Transarterial therapies such as chemoembolization (TACE) and radioembolization (TARE) may be considered for selected patients with liver-dominant metastatic disease. Evidence in breast cancer liver metastases remains limited and heterogeneous, drawn mainly from small studies and systematic reviews rather than large randomized trials, with no established role as a routine replacement for systemic therapy . Suitability is decided through multidisciplinary review involving medical oncology, interventional radiology and, where relevant, hepatobiliary surgery.
Next Steps After Metastatic Breast Cancer Progression
Treatment response is usually described in one of three ways:
- Response: Measurable tumors shrink on imaging.
- Stable disease: The cancer shows no significant growth or shrinkage.
- Progression: Existing tumors grow, or new metastases appear.
Treatment is monitored using imaging, symptoms, and sometimes tumor markers. If progression is confirmed, the next therapy is chosen by weighing the tumor’s biology and the results of any repeat testing, previous treatments, symptoms, potential benefit, side effects, treatment burden, and quality of life.
Treatment Resistance and Further Options
Cancer cells can either fail to respond from the start (primary resistance) or respond initially and then stop responding later (acquired resistance), both reflecting changes in tumor biology. When standard options become limited, clinical trials may be discussed for patients who meet specific eligibility criteria.
Treatment Goals and Quality of Life With Metastatic Breast Cancer
Treatment aims to control or slow the cancer, relieve symptoms, and preserve quality of life and independence for as long as possible. Supportive care including side-effect management, pain relief, nutritional and psychological support, and palliative care is part of treatment from the start, not only when other options run out.
Shared decision-making is central to metastatic care, with patients and their oncology team weighing potential benefits, side effects, and personal priorities when choosing treatment.
Specialist Metastatic Breast Cancer Care in Germany

In Germany, the management of metastatic breast cancer involves individualized treatment planning based on tumor biology, disease progression, previous therapies, and the patient's overall clinical condition. Medical oncologists and other specialists collaborate through multidisciplinary tumor boards to assess diagnostic findings and determine appropriate treatment strategies in accordance with current German and international guidelines [1].
How Is Metastatic Breast Cancer Care Coordinated in Germany?
For international patients seeking treatment in Germany, the process generally begins with a comprehensive review of pathology reports, imaging, biomarker results, and previous treatment records. German specialists use this information to evaluate the disease and discuss suitable options, which may include systemic therapies, radiation therapy, selected surgical interventions, or eligible clinical trials. Recommendations are tailored to the patient's medical history, treatment response, and individual needs.
TIG GmbH (Treatment in Germany) supports international patients by coordinating specialist consultations, organizing medical documentation, and facilitating communication with German hospitals. The treating physicians retain responsibility for diagnosis, treatment recommendations, and all clinical decisions. Treatment eligibility, availability, and timelines depend on individual medical assessments and the services offered by the selected hospital.
The cost of breast cancer in Germany depend on diagnostic tests, medications, procedures, hospital, and duration of care. An individualized estimate requires a review of medical records and the proposed treatment plan. Eligibility for therapies and clinical trials depends on biomarkers, disease characteristics, and previous treatment. Treatment access and outcomes cannot be guaranteed.
References
Why Patients Worldwide Prefer Our Medical Services in Germany – Key Benefits Explained
International patients planning breast cancer treatment in Germany may need support with hospital consultations, medical documentation, translations, and travel arrangements. TIG GmbH helps coordinate these practical steps and communication with healthcare providers according to each patient's needs and the services agreed.

The table above compares the support and coordination services offered through TIG GmbH with the arrangements patients may need to manage when booking directly with a clinic.












.webp)
 (1).webp)

.webp)


.jpg)

 (1).webp)


.jpg)